
AI In Healthcare, Built Around The Clinician's Judgement
Give aged care providers, NDIS providers and health services the capacity to keep up with intake, notes and funder claims, with every clinical and care decision left to a person and every action on the record.

AI You Can Put In Front Of The Board
Built for the questions a quality manager, a board and an auditor will ask, from the first sprint to the quarterly report.
Baseline before build
We time a sample of real cases, map the systems and fix the benchmark in writing before anything is built. After go-live the result is measured against it, so the board paper carries a number the CFO can check.
Governance is a deliverable
Every build comes with the paperwork your compliance and risk people need: where AI is used, who approves what, the audit log and a usage policy they can sign.
Built inside the systems you run
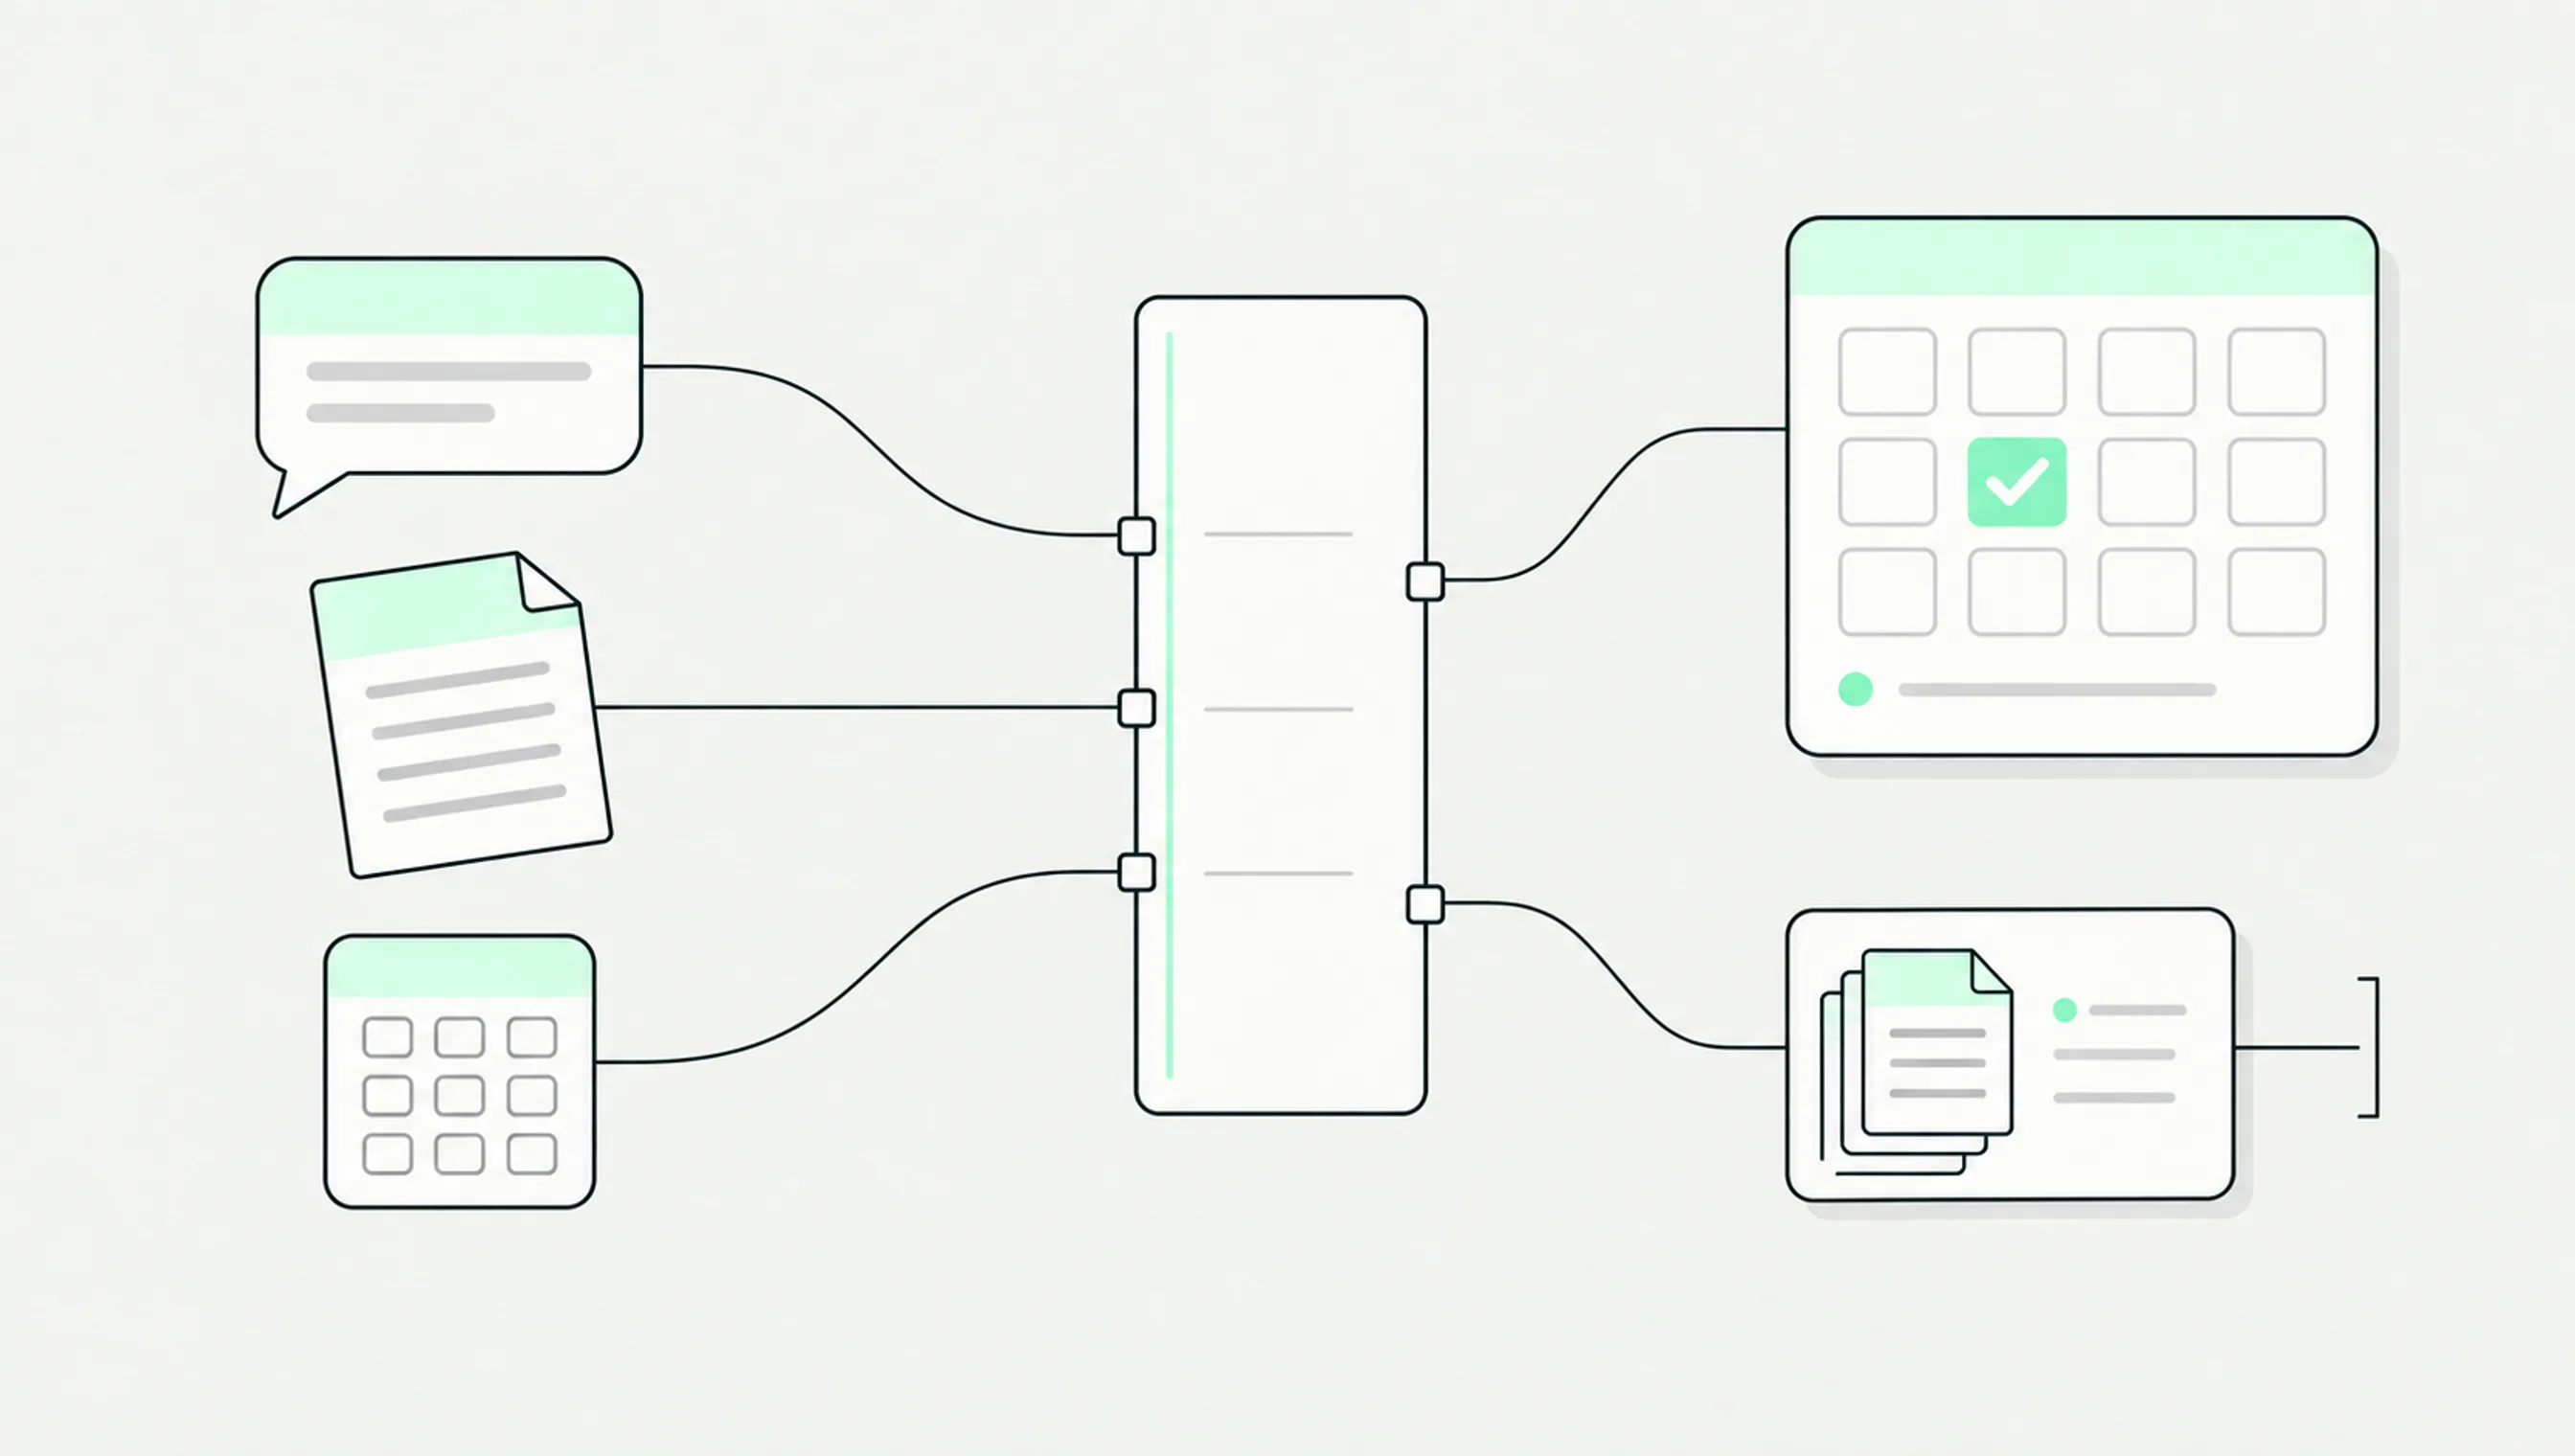
Nothing moves to a new platform. We build around the care management platform, clinical record, rostering system and mailbox you already run. The AI writes back through them with every action on the record.
Built For Every Kind Of Provider
Four kinds of provider, one method. The administration is automated inside the systems each already runs and the person responsible for care keeps every decision.
Aged care providers
Residential and home care providers with intake, care notes and quality evidence to keep current.
NDIS providers
Providers with participant onboarding, service agreements and funder claims to get right first time.
Health services
Clinics and services where the administration around every appointment outweighs the appointment.
Allied health practices
Practices with referrals, reports and claims that a clinician should review rather than assemble.
Transform How The Operation Runs
Capacity, governance and connection. Three things that change, in the order they usually happen.
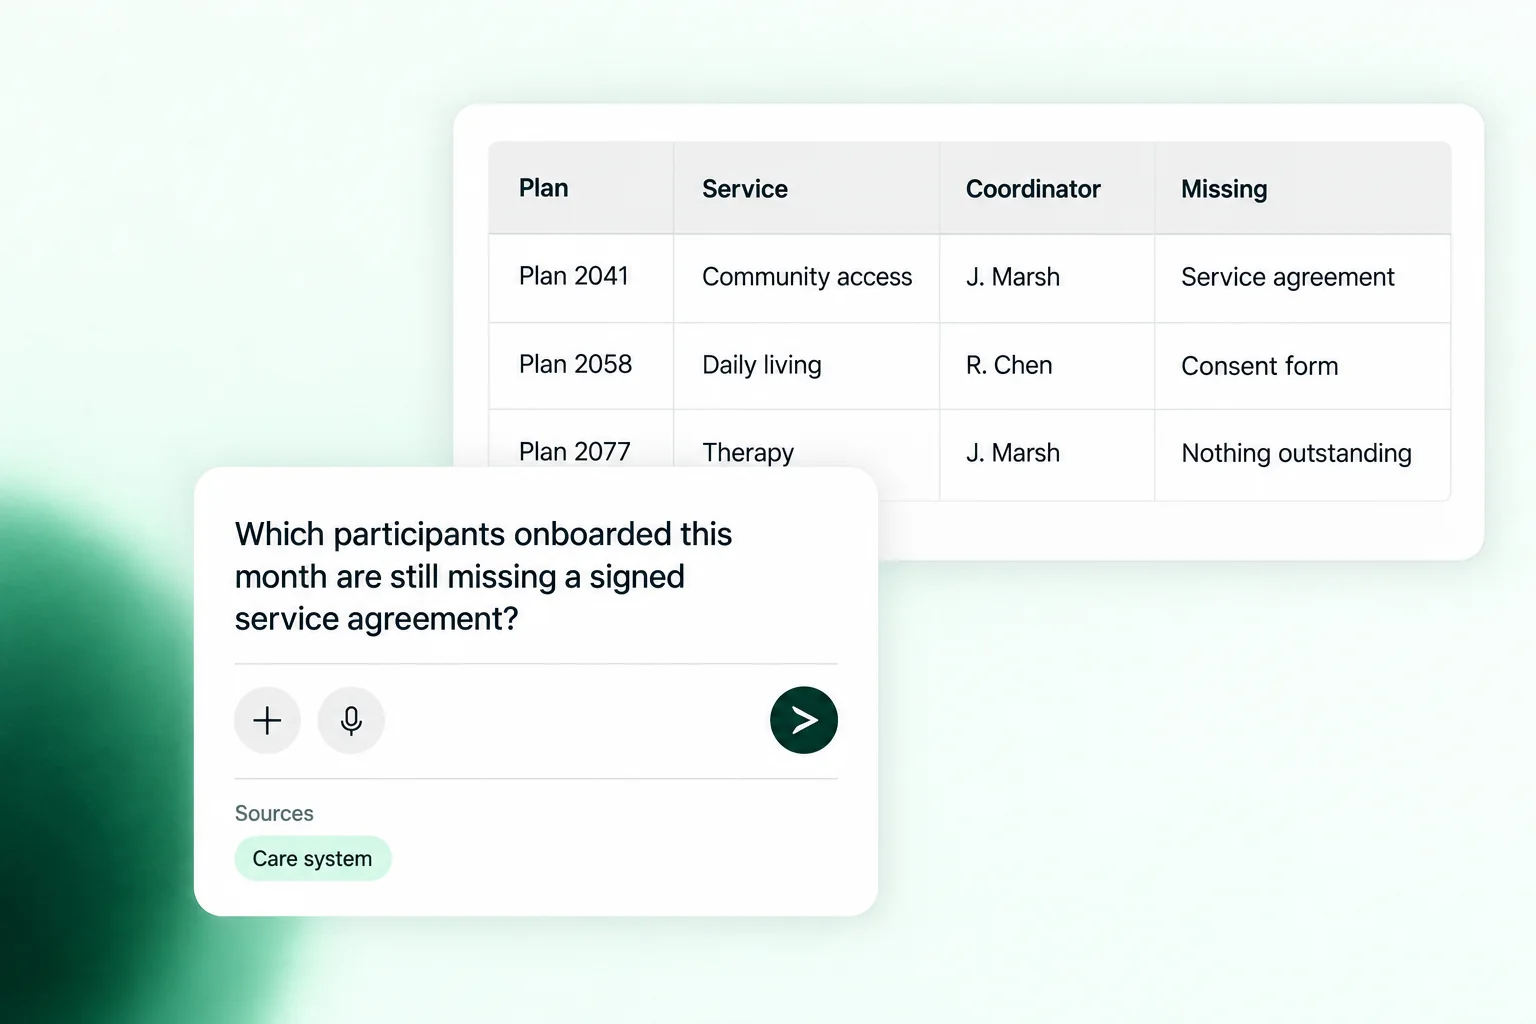
Increase capacity across the service
The AI drafts, checks and holds intake, care notes, incident reports and funder claims for approval, so clinicians and coordinators spend their day with the people in their care.

Govern your AI systems
We keep an inventory of every AI use, map each control to the standard it answers and report every quarter, so the board and the regulator get the same answer.

Connect your care systems
Your care management platform, clinical record and rostering system stay where they are. The AI reads from them and writes back with an audit trail. Nobody learns a new platform.
High-Impact Use Cases For Healthcare And Care
The workflows we automate inside aged care, NDIS providers, health services and allied health practices. The AI handles the administration. The people responsible for care make every decision.
We read the referral, pre-fill the intake form and draft the consents and service agreements, then hold the file until everything is in. A coordinator approves every step.

We read referrals, reports and correspondence, summarise them into the record and check they are complete, with a link back to the source. A person reviews before anything is filed.

We structure shift notes and draft incident reports from the record, then hold them for the responsible person, with the audit trail a quality review will ask for.

We sort the shared mailbox by intent, pull out the key fields, route each item to the right queue and draft a reply where one makes sense. A coordinator reads every draft before it goes anywhere.

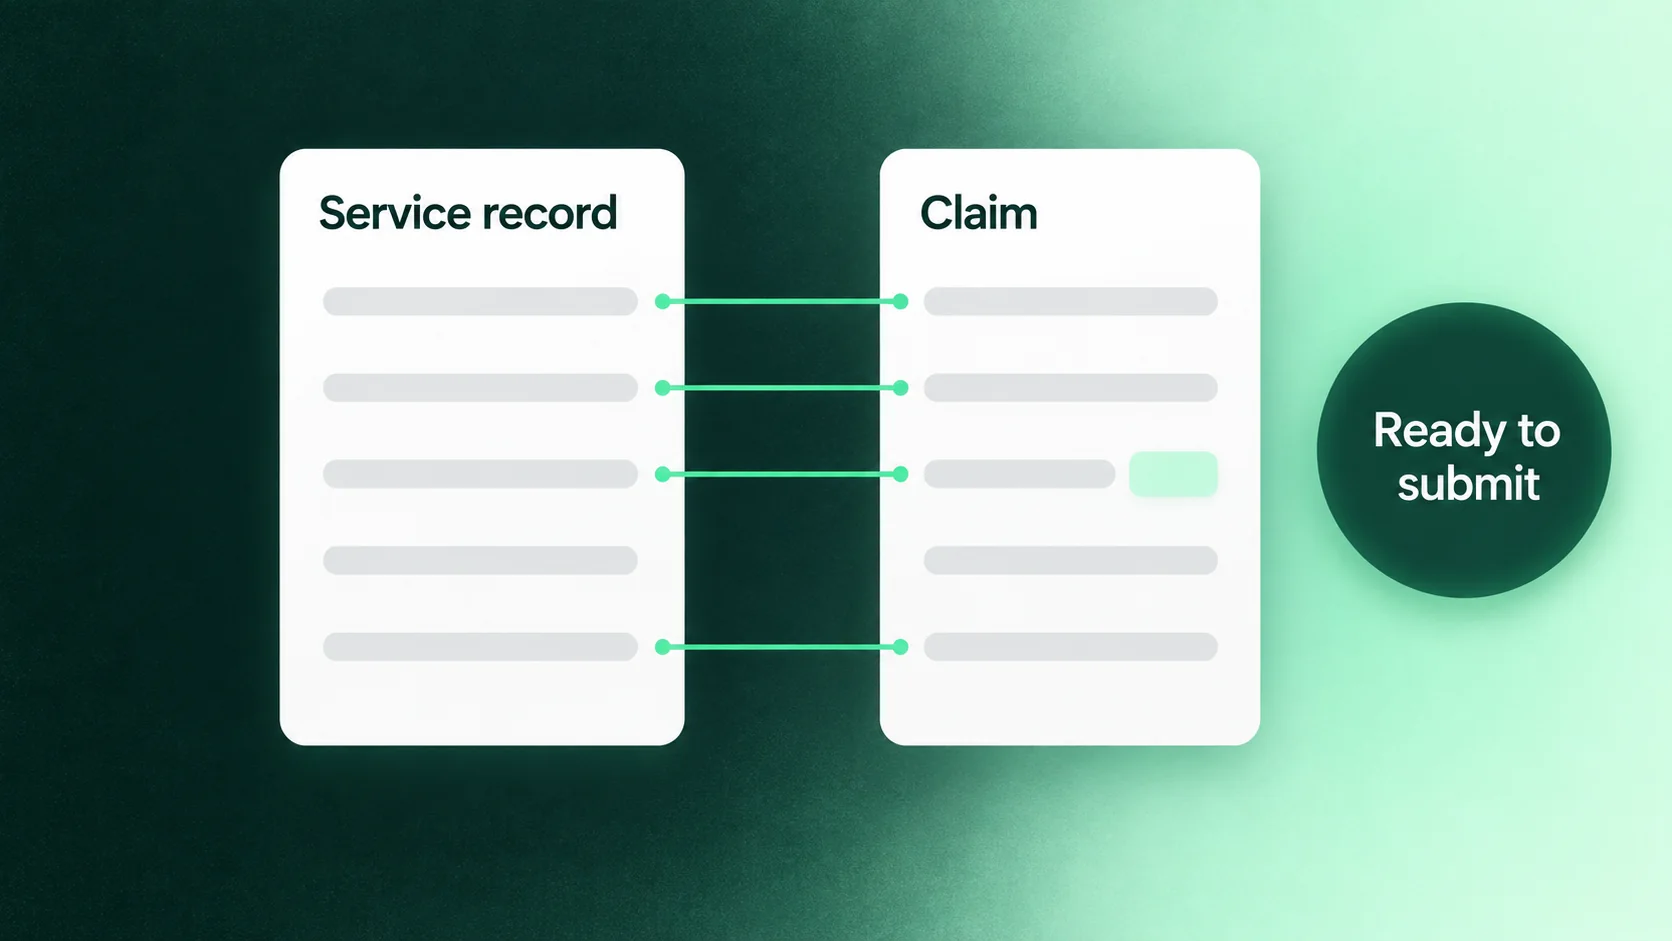
We prepare each claim from the service record, check it against the plan or the schedule and surface the exceptions. A person submits it, so funding arrives on time and reconciles first go.
Health information stays in Australia, with access limited to the people who need it and every record opened on the log. Each build ships with the governance pack your quality and compliance leads sign off on, designed around the quality and safeguarding standards providers answer to, together with health privacy and the consent behind it.

How We Help Healthcare And Care
Care providers and health services exist for the people in their care. The administration around each one keeps growing. Intake, notes, reports and claims take hours that should go to care.
The answer is to apply AI to that administration in the right order, with the controls the quality and privacy regulators expect. We combine AI engineering with people who have worked inside care and health and turn it into workflows a clinician trusts. The levers we pull:
Value creation. We find the intake, reporting and claims work where AI returns the most hours for the least disruption, put a measured number on each before anything is built and prove it against your own baseline after.
Person-centred journeys. We redesign intake, review and communication from the participant's or patient's side, so nothing waits on paperwork and every interaction is on the record.
Downcycle management. When funding tightens and rosters thin, we deliver capacity without headcount. The administration is automated first, so the same team supports more people.
Data analytics and AI. Occupancy, incidents and workload answered in plain language from the systems you already run, with every clinical and care decision kept with a person.
Agile ways of working. We work in short sprints with your own people, shipping one workflow at a time and measuring each, so the operation changes at a pace it can absorb.
Industry experts. Our team has worked alongside clinics and care providers and knows how a service runs day to day. We bring that operating knowledge to every engagement, from the first briefing to the quarterly report.
Reading For Healthcare And Care Leaders
Field notes, regulatory guides and workflow write-ups, grouped by the company type they were written for.
Frequently Asked Questions
The questions healthcare and care leaders ask first, answered in a sentence.
Mostly on the administration. Intake, notes, incident reports, funder claims and the shared inbox. The good implementations keep a clinician or coordinator on every decision and every send. That is where the hours come back to care.
No. It reads, drafts and prepares. Every clinical and care decision stays with the person responsible for it. So does every report that carries their name.
It stays in your environment, hosted in Australia. It is never used to train a model. Access is limited to the people who need it, consent is recorded and every action is logged.
No. We build around what you already run, whether that is your care management platform, clinical record or rostering system. The AI reads from them and writes back through the proper channels.
Evidence. Where AI is used, who is accountable for it, how it is checked and what happens when it gets something wrong. Every build comes with that documentation, written so your quality and risk people can sign it.
With an executive briefing. Sixty to ninety minutes with your leadership team, working through a demonstration on your own records. No cost and no obligation. If it makes sense, we scope a baseline sprint from there.